
- Scientific Area
- Dermatologic surgery
SCIENTIFIC AREA
Skin Cancer Surgery
- DEFINITION
A concise evidence-based justification for skin cancer treatment by a dermatologic surgeon
A dermatologic surgeon should be consulted when a condition primarily involves the skin and requires expert diagnosis together with tissue-preserving surgical management, particularly for skin tumors, cosmetically sensitive sites, recurrent lesions, or cases where optimal functional and aesthetic outcomes are important.
How dermatologic surgeons manage skin cancers?
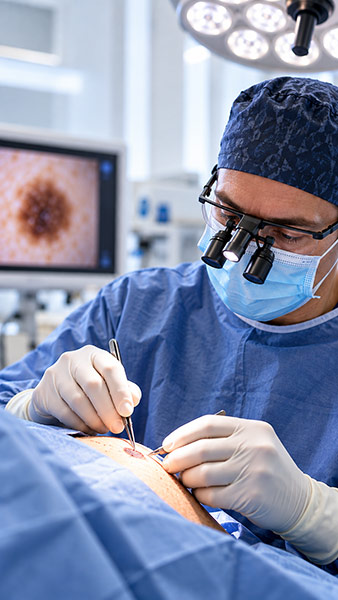
Dermatologic surgeons manage skin cancers through a continuum of care that integrates diagnosis, risk stratification, surgery, reconstruction, pathology correlation, and long-term surveillance.
Their approach differs from many other specialties because treatment is tailored to both tumor biology and anatomic/cosmetic preservation. The process generally follows the following steps:
1. Clinical evaluation and diagnosis
The first step is determining what the lesion is and how aggressive it may be.
This includes:
clinical examination,
dermoscopy,
assessment of growth pattern and symptoms,
review of prior biopsies or treatments,
identification of high-risk features (location, recurrence, immunosuppression, histologic subtype).
Common cancers include:
Basal Cell Carcinoma
Cutaneous Squamous Cell Carcinoma
Melanoma
rarer adnexal or Merkel cell tumors.
A skin biopsy is often performed to establish histologic diagnosis before definitive treatment.
2. Risk stratification
Dermatologic surgeons do not treat all skin cancers the same way. Management depends on:
tumor type,
size and depth,
histologic aggressiveness,
anatomic location,
whether it is primary or recurrent,
patient factors (age, anticoagulation, immunosuppression).
For example, a small low-risk basal cell carcinoma on the trunk may be managed very differently from an infiltrative tumor on the nose.
3. Selection of the most appropriate treatment
Treatment is always individualized.
Standard surgical excision
For many tumors, the lesion is removed with a predefined margin of clinically normal skin. The specimen is then sent for pathology to confirm:
complete removal,
subtype,
margin status.
This is common for lower-risk tumors.
Mohs micrographic surgery
For high-risk tumors or anatomically sensitive tumors, dermatologic surgeons may perform Mohs micrographic surgery.
This technique:
removes the cancer in stages,
examines 100% of peripheral and deep margins during the procedure,
repeats removal only where cancer remains.
It is especially valuable for:
nose,
eyelids,
lips,
ears,
recurrent cancers,
aggressive histologic subtypes.
The main advantages are:
very high cure rates,
maximal tissue preservation,
smaller defects,
improved cosmetic and functional outcomes.
4. Reconstruction after tumor removal
Once the cancer is cleared, reconstruction is planned. Options include:
healing by secondary intention,
direct closure,
skin flaps,
skin grafts,
staged reconstruction when needed.
The goal is not only closure but also:
preservation of function,
minimal distortion,
optimal scar placement,
aesthetic integration with surrounding skin,
as minimally visible scars as technically possible.
For example, nasal or eyelid reconstruction requires preservation of breathing, blinking, and facial symmetry.
5. Non-surgical or adjuvant treatments (selected cases)
Dermatologic surgeons may also integrate:
cryotherapy,
curettage and electrodessication,
topical medical therapies,
photodynamic therapy,
laser techniques,
systemic therapies, mostly in coordination with medical oncology and radiation therapist,
multi-specialty tumor board coordination of care of more complex and advised cases.
This may occur when surgery is not ideal or as adjunctive care.
6. Surveillance and prevention
Skin cancer care does not end with excision. Dermatologic surgeons typically provide:
recurrence monitoring,
full-body skin examinations,
management of precancerous lesions,
risk reduction counseling,
early detection of new primary cancers.
Patients with one skin cancer have indeed an increased risk of developing additional lesions.
Why this model is distinctive
The dermatologic surgery model combines:
diagnosis → pathology-guided treatment → tissue-sparing surgery → reconstruction → long-term skin surveillance
Stay connected with ISDS
Get the latest news, events and educational opportunities.